Current Approach to Coronary Calcium Management with Tips and Tricks
www.google.com
Nov. 7, 2026, 5:08 a.m.
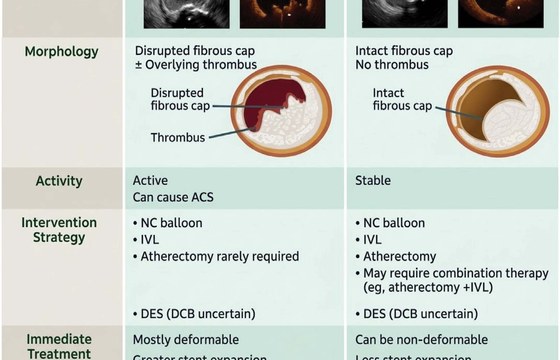
Coronary artery calcification represents a critical challenge in percutaneous coronary intervention, significantly impacting procedural success and long-term patient outcomes. Calcium deposits obstruct device delivery, cause incomplete stent expansion, damage drug coatings, and increase risks of stent thrombosis, restenosis, and target-lesion revascularization. Contemporary management has evolved from angiography-based approaches toward morphology-specific strategies utilizing intravascular imaging technologies. Optical coherence tomography and intravascular ultrasound enable precise assessment of calcium characteristics including arc, thickness, length, and nodule presence. Validated imaging scores predict underexpansion and guide treatment selection. The expanded toolkit includes noncompliant, cutting, scoring, and super-high-pressure balloons; rotational and orbital atherectomy; intravascular lithotripsy; and excimer laser coronary atherectomy. Strategic combinations of these interventions optimize outcomes by addressing the specific morphological features identified through advanced imaging, fundamentally improving procedural efficacy and reducing adverse complications in calcified coronary lesions.
Expanding physiology beyond the wire: will 2026 be the defining year?
www.google.com
Nov. 7, 2026, 5:08 a.m.
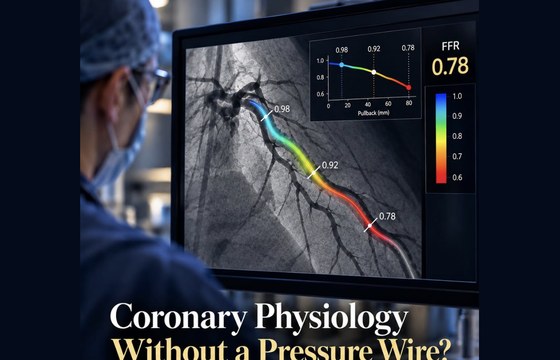
Coronary lesion functional assessment is essential for guiding percutaneous coronary intervention decisions, yet wire-based fractional flow reserve (FFR) adoption remains limited due to cost, complexity, and procedural demands. Angiography-derived physiological indices, particularly quantitative flow ratio (QFR), offer promising alternatives by eliminating the need for pressure wires and pharmacological hyperaemia induction while enabling virtual pullback analysis to distinguish focal from diffuse disease. QFR potentially expands physiology-guided revascularisation accessibility, especially in centers with low pressure wire utilization. The FAVOR III Europe trial's two-year follow-up, reported in EuroIntervention, provides crucial validation data examining whether QFR-guided revascularisation matches FFR-guided outcomes. This research represents more than a simple device comparison; it tests whether physiological assessment can be democratized across interventional laboratories without sacrificing patient outcomes. The trial's findings will significantly influence whether angiography-derived FFR becomes standard practice, potentially transforming how interventional cardiologists approach revascularisation planning globally.
When Does a Calcified Heart Blockage Need Advanced Angioplasty?
www.google.com
Nov. 7, 2026, 5:07 a.m.
Calcified coronary artery blockages present unique treatment challenges that require individualized assessment rather than standardized approaches. While some calcium deposits can be managed with conventional balloon angioplasty and stenting, severe or extensive calcification may necessitate advanced techniques and careful lesion preparation to ensure proper stent expansion. Treatment decisions consider multiple factors beyond calcium presence, including blockage severity and location, calcium pattern and amount, artery condition, patient symptoms, and heart function. Heavily calcified arteries become rigid, potentially preventing adequate balloon expansion and stent deployment. Intravascular imaging plays a crucial role in treatment planning, with IVUS using ultrasound technology and OCT employing light-based imaging to provide detailed vessel and calcium assessment. These techniques help cardiologists understand vessel characteristics and calcium distribution, enabling more precise treatment planning. The key distinction is that calcium alone does not automatically warrant advanced angioplasty; rather, treatment selection depends on whether calcium significantly interferes with balloon expansion or stent delivery in the specific patient's artery, ensuring optimal clinical outcomes.
Share on
Tools & Techniques: PCI in coronary bifurcations lesions
www.google.com
Nov. 7, 2026, 5:07 a.m.
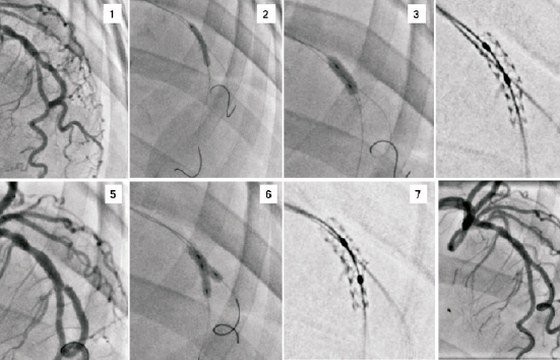
Coronary bifurcation lesions represent a common clinical challenge in interventional cardiology, occurring frequently due to low wall shear stress in areas opposite the carina of bifurcations. This professional overview presents a comprehensive, step-wise approach to percutaneous coronary intervention in bifurcation lesions, with detailed discussion available in the complete e-version at EuroIntervention. The coronary tree follows fractal geometry principles, with bifurcations governed by Murray's law and Finet's formula, which establishes the diameter relationship between the main vessel and distal branches. The Medina classification serves as the primary descriptive tool for bifurcation lesions, indicating the location of significant stenosis greater than fifty percent across proximal main vessel, distal main vessel, and side branch segments. Among multiple treatment techniques encompassed in the MADS classification, provisional side branch stenting has emerged as the gold standard strategy for non-left main bifurcation treatment. Six of seven randomized trials comparing this approach with dual-stent techniques demonstrated that implanting two stents provides no additional benefits regardless of lesion type, establishing provisional side branch stenting as the preferred interventional strategy.
Share on
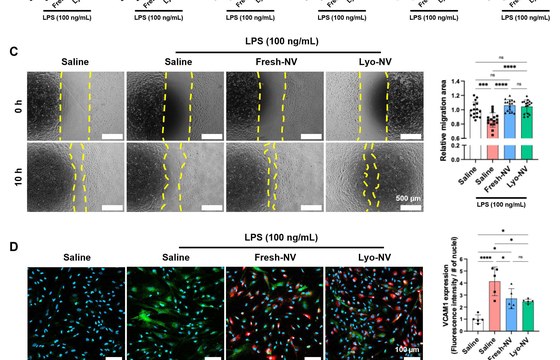
Therapeutic decoupling of restenosis prevention from impaired vascular healing with regenerative nanovesicle-eluting bioresorbable scaffolds
www.thno.org
Nov. 7, 2026, 5:06 a.m.
Researchers from multiple institutions across South Korea and Canada have developed a novel therapeutic approach to address a longstanding clinical challenge in stent-based vascular interventions. The study, published in Theranostics, tackles the inherent conflict between preventing restenosis and promoting healthy vascular healing following stent placement. Traditional drug-eluting stents effectively reduce neointimal hyperplasia by suppressing vascular smooth muscle cell proliferation, yet their cytostatic mechanisms inadvertently impede re-endothelialization and compromise the vessel's natural repair processes. This therapeutic tradeoff has limited clinical outcomes for patients undergoing revascularization procedures. The research team investigated a regenerative scaffold strategy designed to decouple restenosis prevention from the detrimental effects on vascular healing. By separating these competing biological demands through an innovative scaffold-based platform, the investigators aimed to maintain antirestenotic efficacy while simultaneously facilitating proper endothelial recovery and tissue repair. This advancement represents a significant step toward improving long-term outcomes in percutaneous coronary intervention by enabling both effective restenosis suppression and optimal vascular healing, potentially reducing restenosis rates and patient complications while maintaining the therapeutic benefits of current stent technologies.
Share on
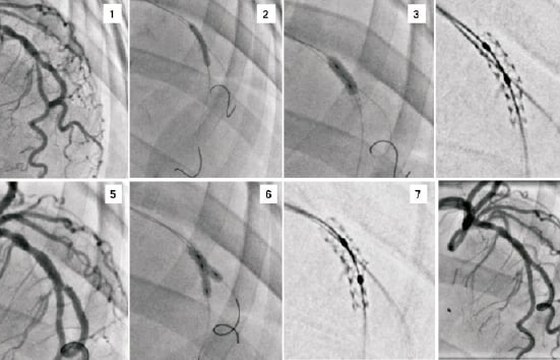
Tools & Techniques: PCI in coronary bifurcations lesions
eurointervention.pcronline.com
Nov. 3, 2026, 12:50 p.m.
Coronary bifurcation lesions are common in clinical practice due to low wall shear stress areas present in both branches opposite the carina. This professional overview presents a comprehensive step-wise approach to percutaneous coronary intervention (PCI) in bifurcation lesions, with particular emphasis on provisional side branch (SB) stenting as the gold standard technique. The article establishes anatomical context using Murray's law and Finet's formula, which define the diameter relationships between main vessels and distal branches according to principles of fractal geometry. The Medina classification is introduced as a descriptive tool for characterizing bifurcation lesions based on stenosis location, though it cannot account for angles, calcifications, or lesion length. The MADS classification summarizes various treatment techniques available for bifurcation intervention. Evidence from six of seven randomized trials demonstrates that provisional SB stenting outperforms dual-stent strategies regardless of lesion type, establishing it as the preferred approach for non-left main bifurcation treatment. The systematic analysis provided addresses the substantial ongoing debate regarding optimal technical strategies in bifurcation intervention and provides detailed guidance for interventional cardiologists managing these complex lesions.
Share on
Volume 22 Number 20 | EuroIntervention
eurointervention.pcronline.com
Nov. 3, 2026, 12:49 p.m.
This issue of EuroIntervention presents a comprehensive collection of clinical research addressing contemporary interventional cardiology challenges. The journal features original research examining coronary artery disease management strategies in transcatheter aortic valve implantation (TAVI) patients, alongside investigations into prolonged inflation techniques for balloon-expandable TAVI devices to optimize procedural outcomes. Early clinical findings are presented on left-sided AngioVac utilization, a mechanical thrombectomy system for treating pulmonary embolism. Notably, the SPIRARE II trial reports pivotal results for the Vertex Pulmonary Embolectomy System, representing a significant advance in catheter-based PE intervention. Additionally, the journal publishes research correspondence examining life expectancy outcomes following aortic valve replacement procedures. This multifaceted research portfolio reflects the field's evolving focus on refining TAVI techniques, expanding mechanical circulatory support options, and improving long-term patient outcomes. These studies collectively contribute important clinical evidence to guide interventional practices and inform treatment decision-making for complex valvular and thromboembolic conditions in contemporary practice.
Share on
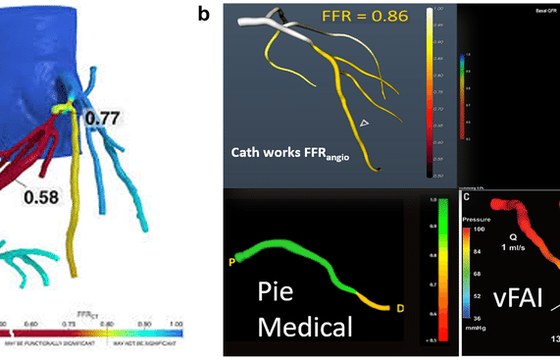
Angiography-derived versus wire-based fractional flow reserve for guiding coronary revascularization: a meta-analysis of randomized controlled trials
www.frontiersin.org
Nov. 3, 2026, 12:49 p.m.
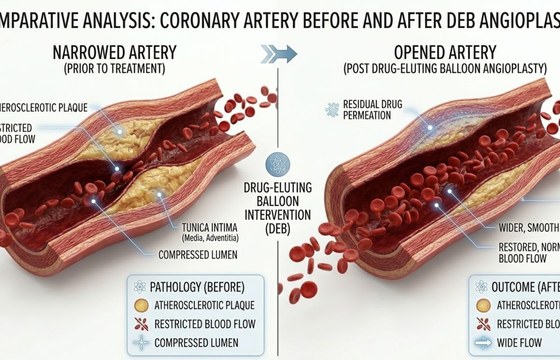
Researchers conducted a systematic review and meta-analysis comparing angiography-derived fractional flow reserve (FFR) with traditional wire-based FFR for guiding coronary revascularization decisions. Analyzing four randomized controlled trials encompassing 6,542 participants, they found no significant differences in major adverse cardiovascular events, all-cause mortality, cardiac mortality, myocardial infarction recurrence, unplanned revascularization, or stent thrombosis between the two approaches. However, angiography-derived FFR was associated with higher patient-level and lesion-level percutaneous coronary intervention (PCI) rates and shorter procedural times. The angiography-derived method offers a non-invasive alternative to wire-based FFR, eliminating the need for specialized pressure-wire equipment and adenosine-induced hyperemia. While the findings demonstrate clinical safety equivalence, the higher PCI rates suggest potential for increased unnecessary interventions. The authors emphasize that trial sequential analysis revealed insufficient sample sizes for most hard clinical endpoints, necessitating larger, longer-term studies to fully understand the long-term implications of using angiography-derived FFR for revascularization guidance.
Volume 22 Number 19 | EuroIntervention
eurointervention.pcronline.com
Nov. 3, 2026, 12:49 p.m.
This issue of EuroIntervention presents several significant contributions to interventional cardiology research. Key studies examine sirolimus-eluting balloon percutaneous coronary intervention as a treatment option for patients at high bleeding risk, addressing an important clinical need for populations who cannot tolerate standard dual antiplatelet therapy. Additional research explores the complexity of coronary disease presentation in patients experiencing infarct-related cardiogenic shock, a critically ill population requiring specialized intervention strategies. The journal also features investigations into device success assessment methodologies following PCI procedures, providing clinicians with improved evaluation frameworks. Research correspondences contribute focused insights on calcium density progression within coronary lesions and the remodeling patterns of chronic total occlusion vessels, both advancing understanding of atherosclerotic disease behavior. Collectively, these papers expand the evidence base for managing challenging patient populations and complex anatomical presentations in interventional cardiology, with particular emphasis on optimizing outcomes in high-risk scenarios and improving procedural assessment techniques.
Share on
Drug-Coated Balloons in Contemporary Coronary
kosuyoluheartjournal.com
Nov. 3, 2026, 12:49 p.m.
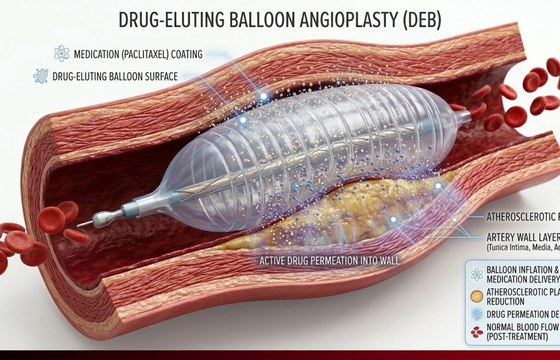
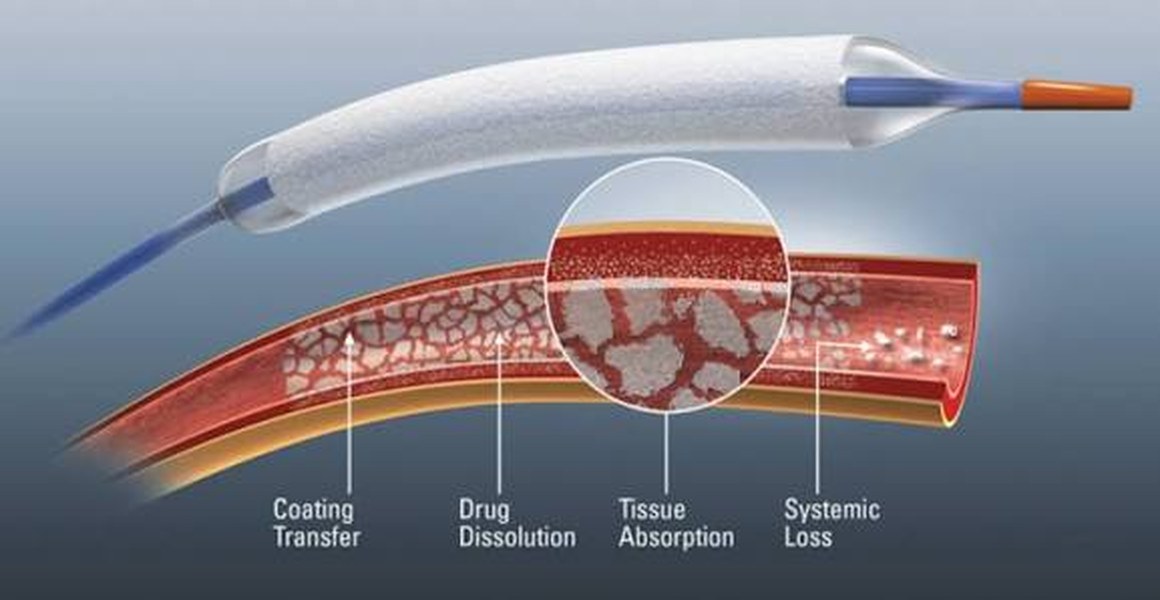
Drug-coated balloons represent an innovative advancement in contemporary coronary intervention, offering a minimally invasive alternative to traditional stent placement for treating coronary artery disease. This technology combines percutaneous balloon angioplasty with localized drug delivery, where antiproliferative agents are applied directly to the vessel wall to inhibit restenosis. The approach addresses a critical clinical challenge: preventing the abnormal smooth muscle cell proliferation that leads to vessel renarrowing following intervention. Drug-coated balloons deliver medications such as paclitaxel directly at the lesion site, achieving therapeutic concentrations while minimizing systemic exposure. This technique proves particularly valuable for patients with small-vessel disease, in-stent restenosis, and those requiring preservation of future intervention options. Clinical evidence demonstrates reduced rates of target lesion revascularization and improved long-term patency compared to conventional balloon angioplasty alone. The technology's significance lies in expanding treatment options for complex coronary pathology while reducing procedural morbidity and potentially improving quality of life through fewer repeat interventions and reduced medication burden for patients.
Comparisons of early vascular reactions in biodegradable and durable polymer-based drug-eluting stents in the porcine coronary artery
journals.plos.org
Nov. 3, 2026, 6:29 a.m.
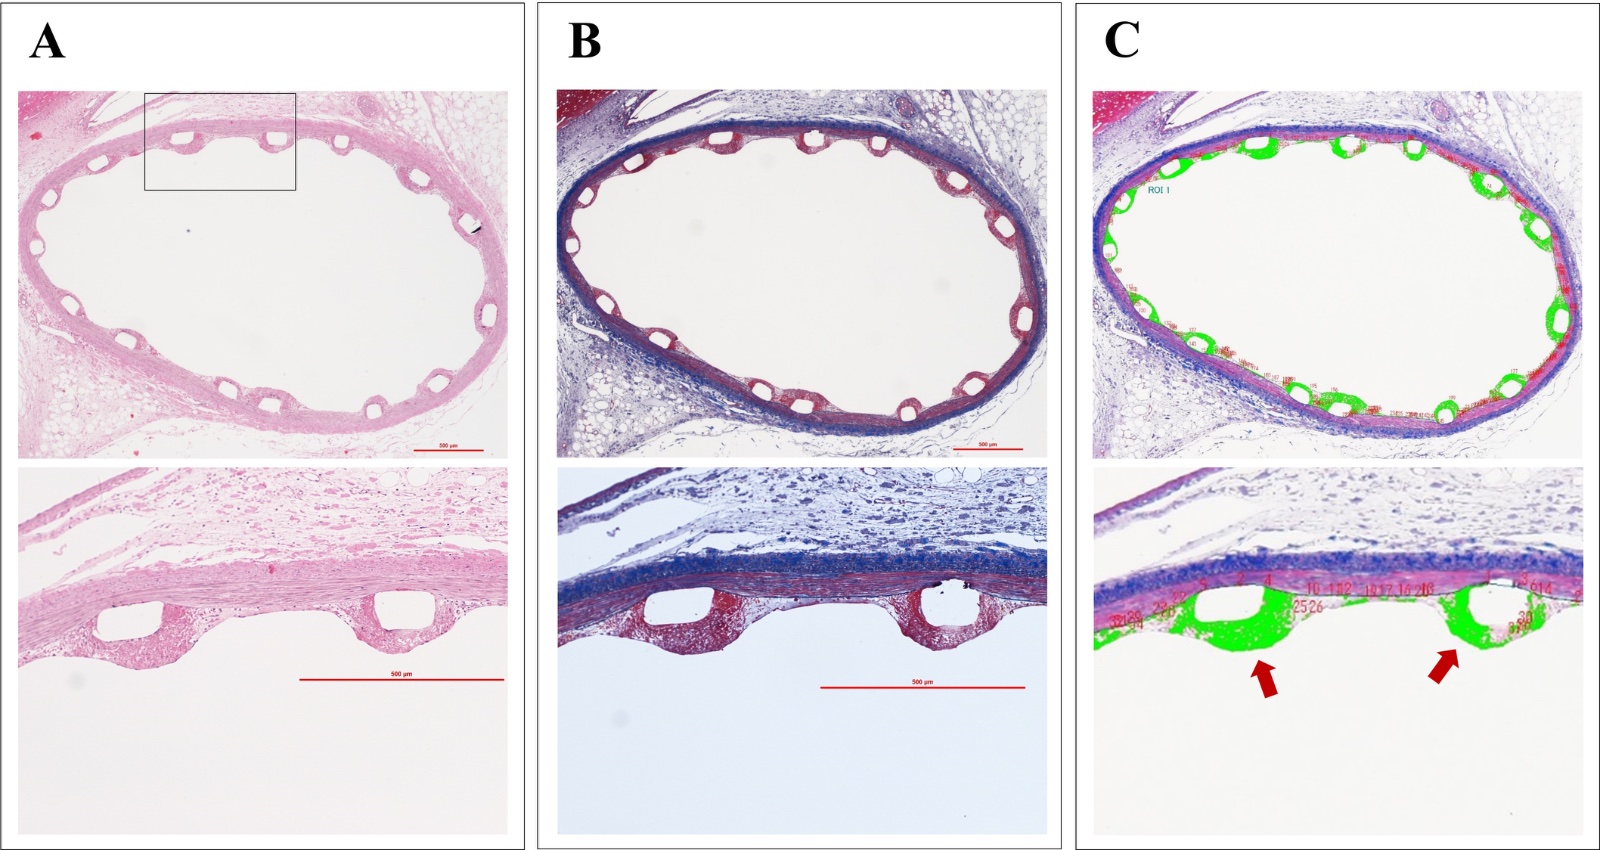
Stent thrombosis (ST) is known as a fatal complication after percutaneous coronary intervention [1, 2]. Although delayed endothelial healing was considered to be the main cause of a late ST for the first generation of drug-eluting stents (DES), recent studies hypothesized that an abnormal vascular reaction, such as neoatherosclerosis and severe inflammation, contributed to a very late ST [3, 4]. However, despite the dramatic improvement of arterial healing for newer DES [5], early ST is still observed in a clinical setting. Therefore, it is important to understand the early vascular reaction that leads to ST. In patients presenting with early ST, Nakano et al. demonstrated that necrotic core prolapse, medial tear and incomplete strut apposition were associated with the occurrence of ST [6].
Share on
Between Scylla and Charybdis: Navigating the dilemma of bleeding and stroke
www.pcronline.com
Oct. 31, 2026, 7:29 p.m.
An 86-year-old woman with atrial fibrillation develops a retinal haemorrhage while receiving anticoagulation, only to suffer a disabling ischaemic stroke weeks after dose reduction. Faced with the challenge of balancing stroke prevention against bleeding risk, what would be your treatment strategy?
Share on
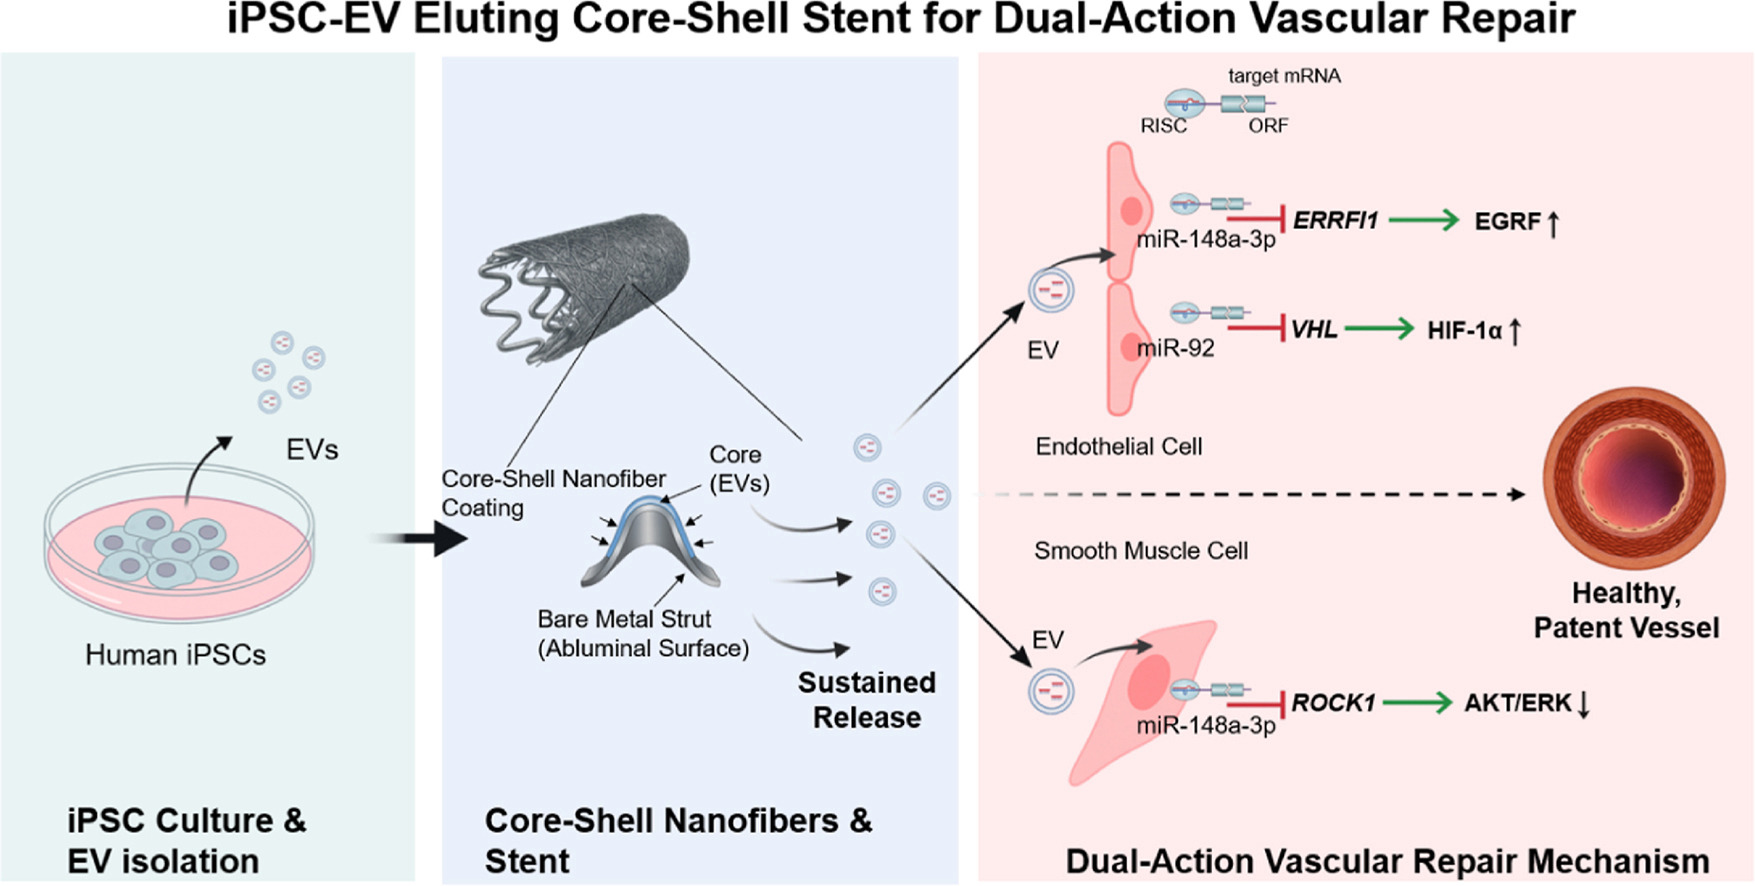
Human iPSC-EV-loaded nanofiber stent coatings accelerate vascular repair by enhancing EGFR/HIF-1α signaling and suppressing ROCK1-mediated remodeling
www.sciencedirect.com
Oct. 28, 2026, 7:16 p.m.
Human induced pluripotent stem cell–derived extracellular vesicles (EVs) were released in a controlled manner from core-shell nanofibrous membranes coated onto a bare metal stent. This localized EV delivery strategy accelerated endothelial regeneration while inhibiting excessive smooth muscle cell proliferation.
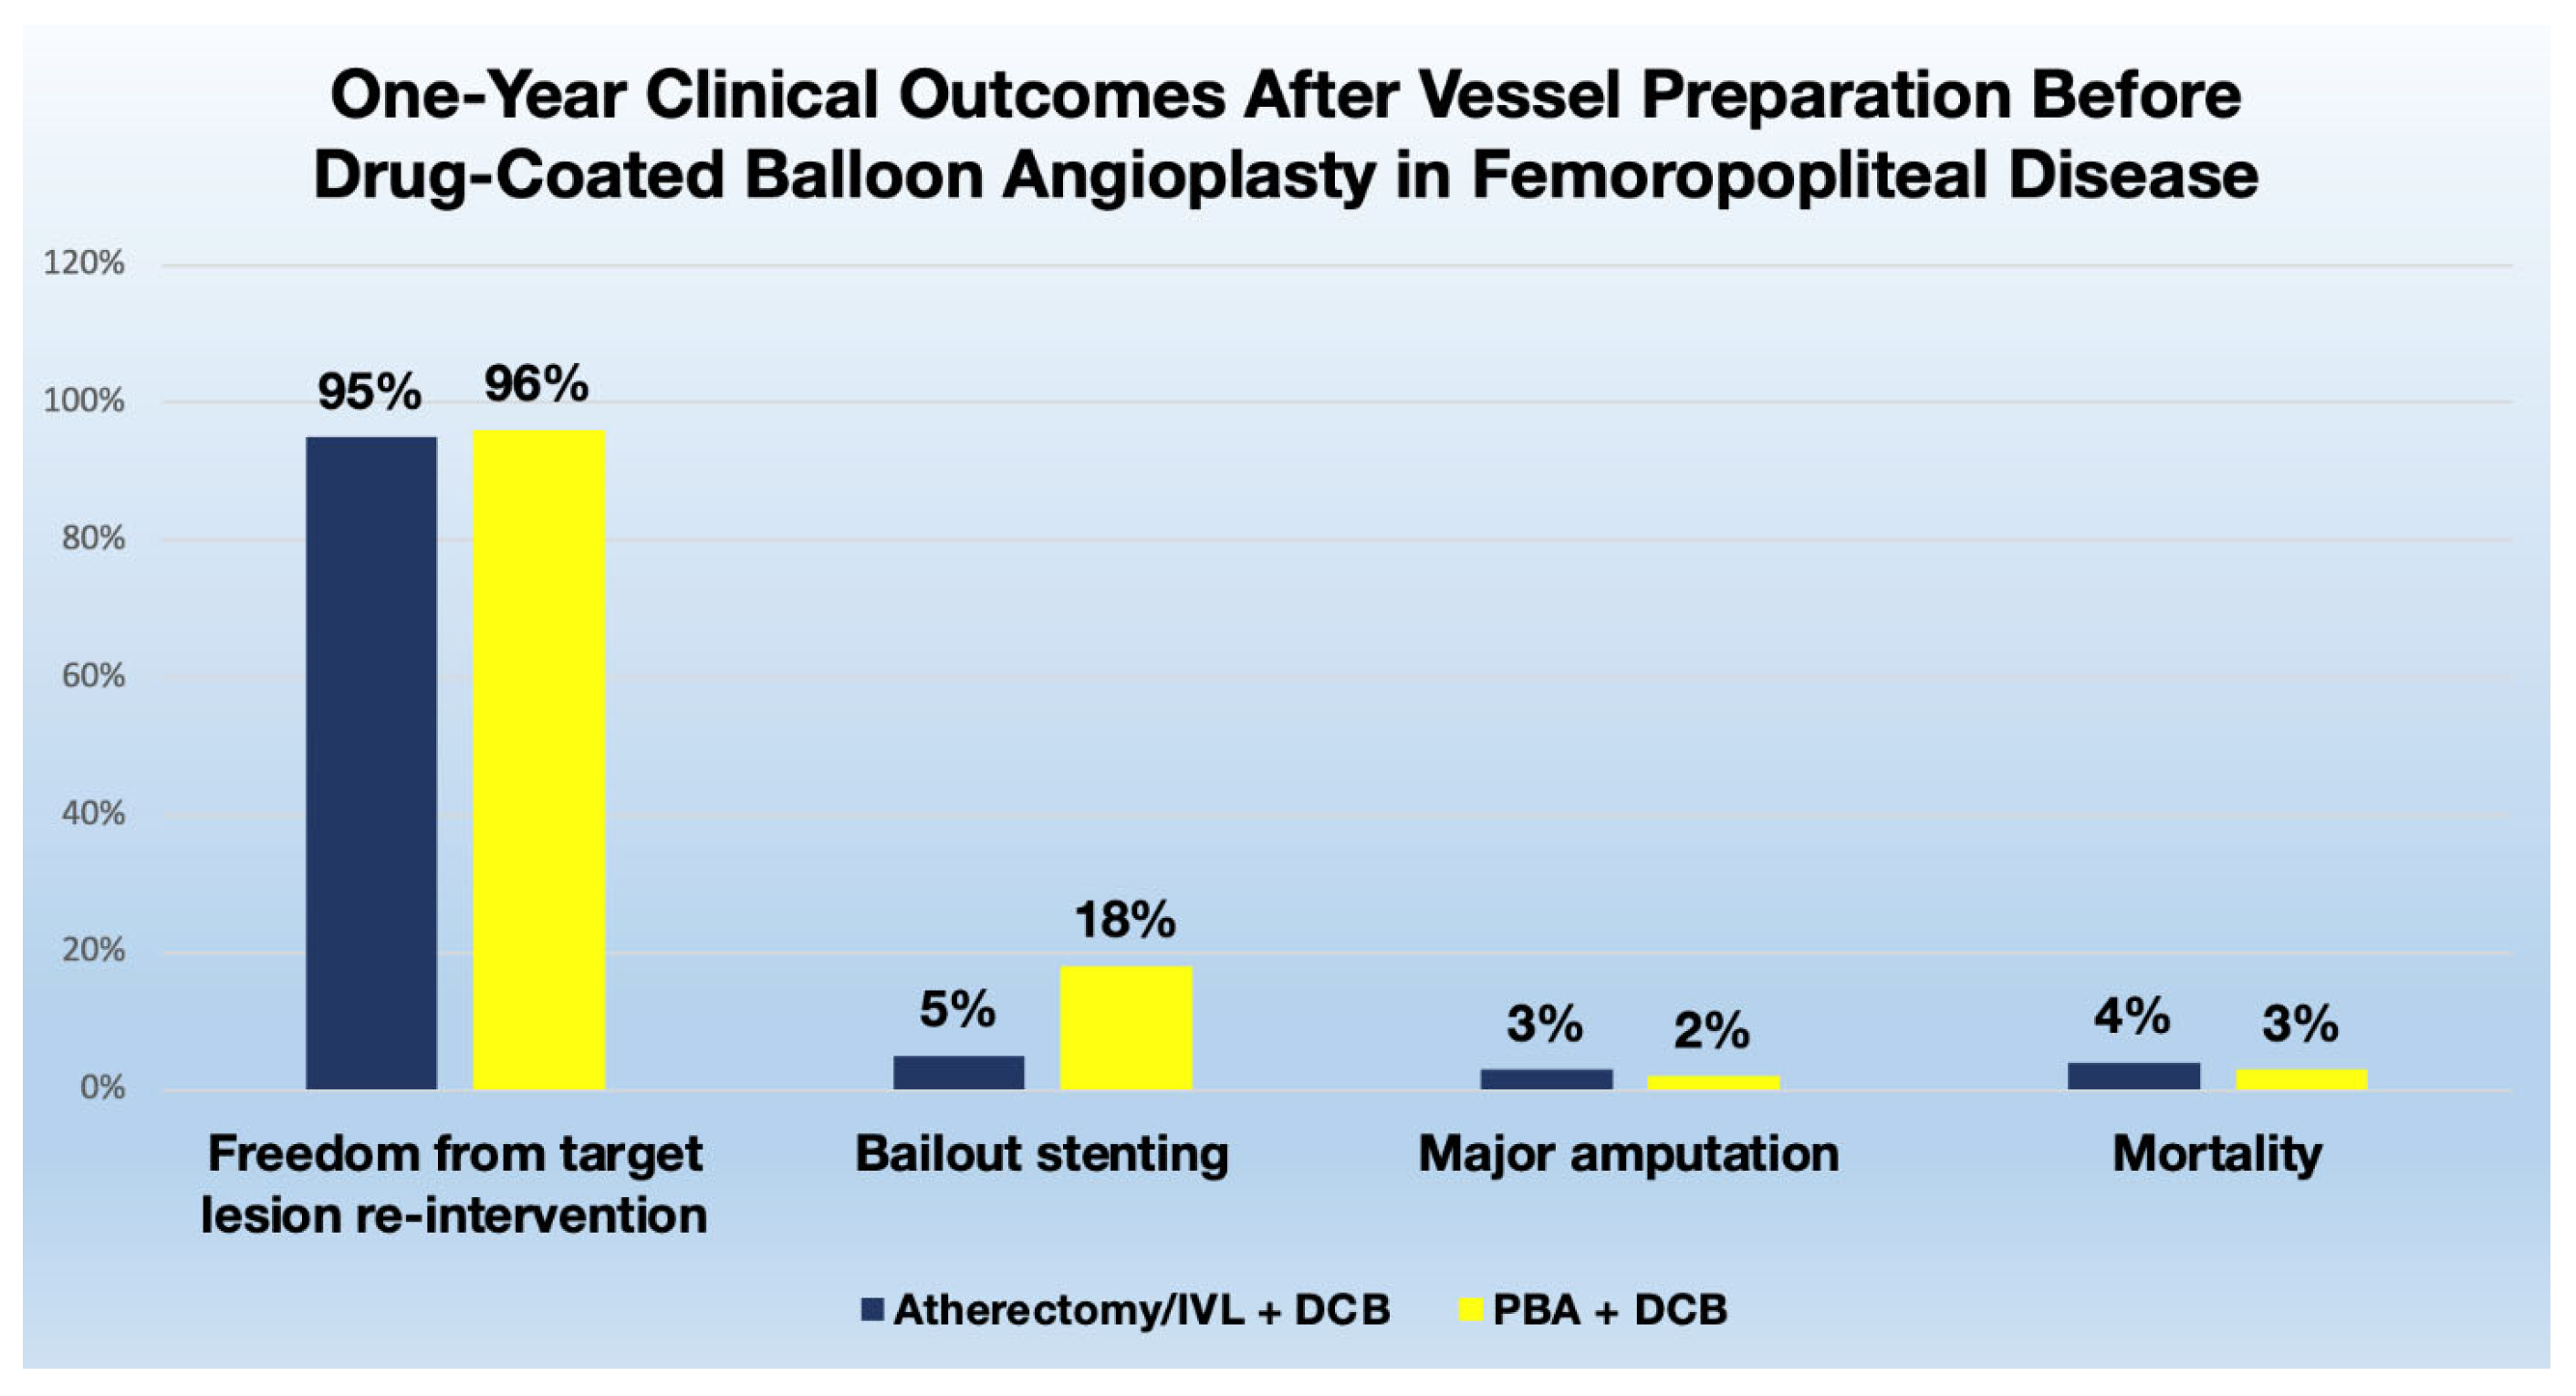
Optimizing Drug-Coated Balloon Outcomes: The Evolving Role of Vessel Preparation in Coronary and Peripheral Artery Interventions
www.mdpi.com
Oct. 28, 2026, 7:15 p.m.
DCB therapy in both coronary and peripheral disease is facilitated by achieving a predictable treatment substrate rather than maximal lesion modification. Thus, vessel preparation should be lesion and vessel specific, overcoming the primary mechanical constraint and enabling appropriate expansion, controlled injury, and effective balloon–vessel contact. The longevity of DCB in coronary disease may be influenced by residual plaque burden, calcium morphology, and vessel-wall features, while residual stenosis, recoil, and flow-limiting dissection are more closely related to peripheral results. Atherectomy and IVL may enhance procedural success and lesion reduction but their incremental influence on long-term DCB-specific outcomes is unknown. Future trials should establish objective, imaging-based preparation targets and determine whether achieving a “DCB-ready” vessel improves drug delivery and durable clinical outcomes. Ultimately, the goal is not to select the most advanced preparation device, but to identify the least aggressive strategy that reliably prepares the vessel for successful DCB therapy.
Share on
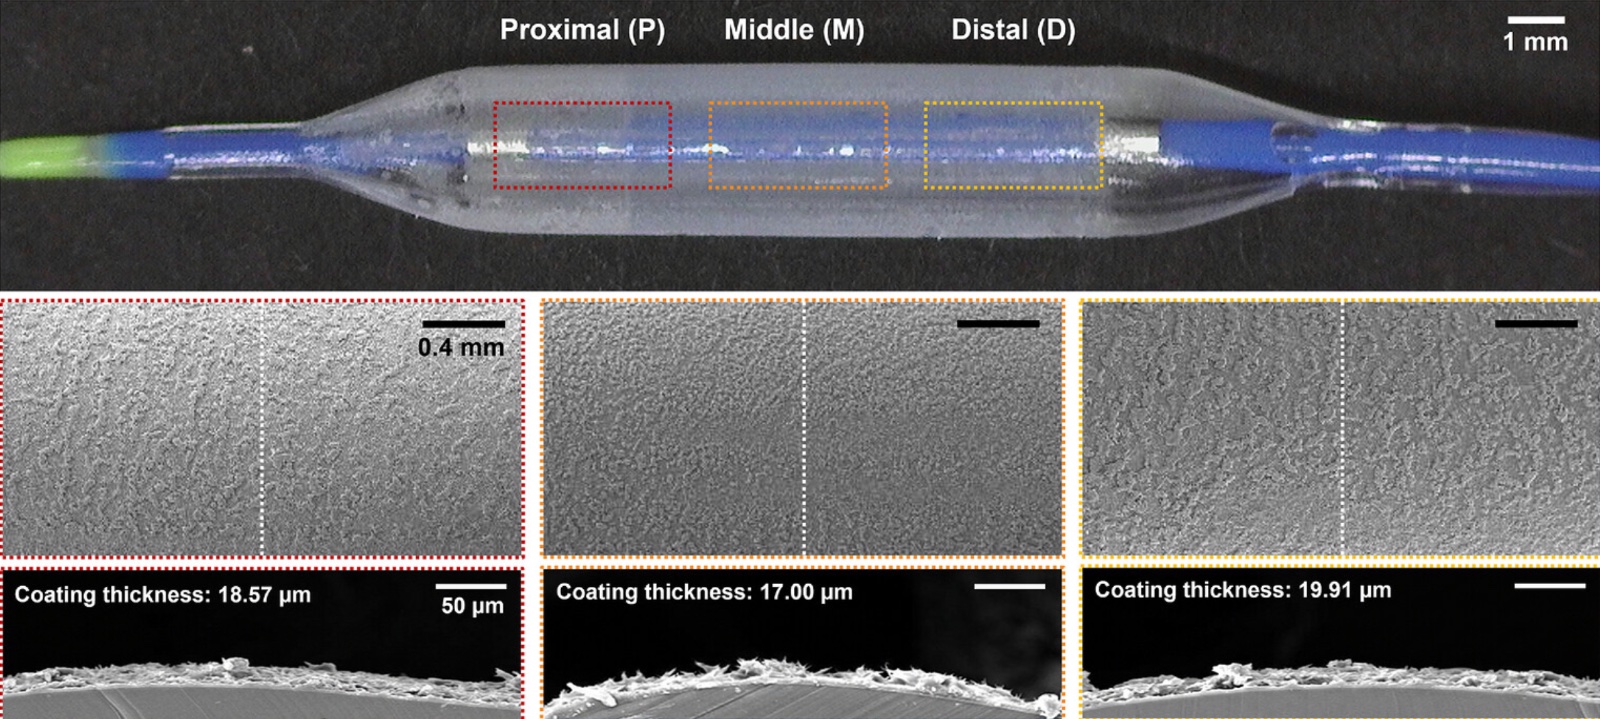
Pressure‐Assisted Drug Delivery Using High‐Pressure Balloon Platform Improves Vascular Drug Penetration and Anti‐Restenotic Effects
advanced.onlinelibrary.wiley.com
Oct. 28, 2026, 7:13 p.m.
High-pressure drug-coated balloon (HP@DCB) angioplasty enhances vascular drug delivery by overcoming the limitations of passive diffusion-based conventional noncompliant DCB (NC@DCB) systems. We developed a dual-layer HP balloon catheter composed of an outer Nylon 12 layer and an inner Pebax 7233 layer, and evaluated its feasibility and therapeutic efficacy as a paclitaxel (PTX)-coated platform. Shellac-based PTX coating was uniformly applied to HP@DCB and NC@DCB, and coating thickness, drug amount, release behavior, and mechanical properties were compared. Pressure-assisted drug penetration was assessed in a vascular-mimicking agarose gel phantom using fluorescent PTX and confocal microscopy.
Share on
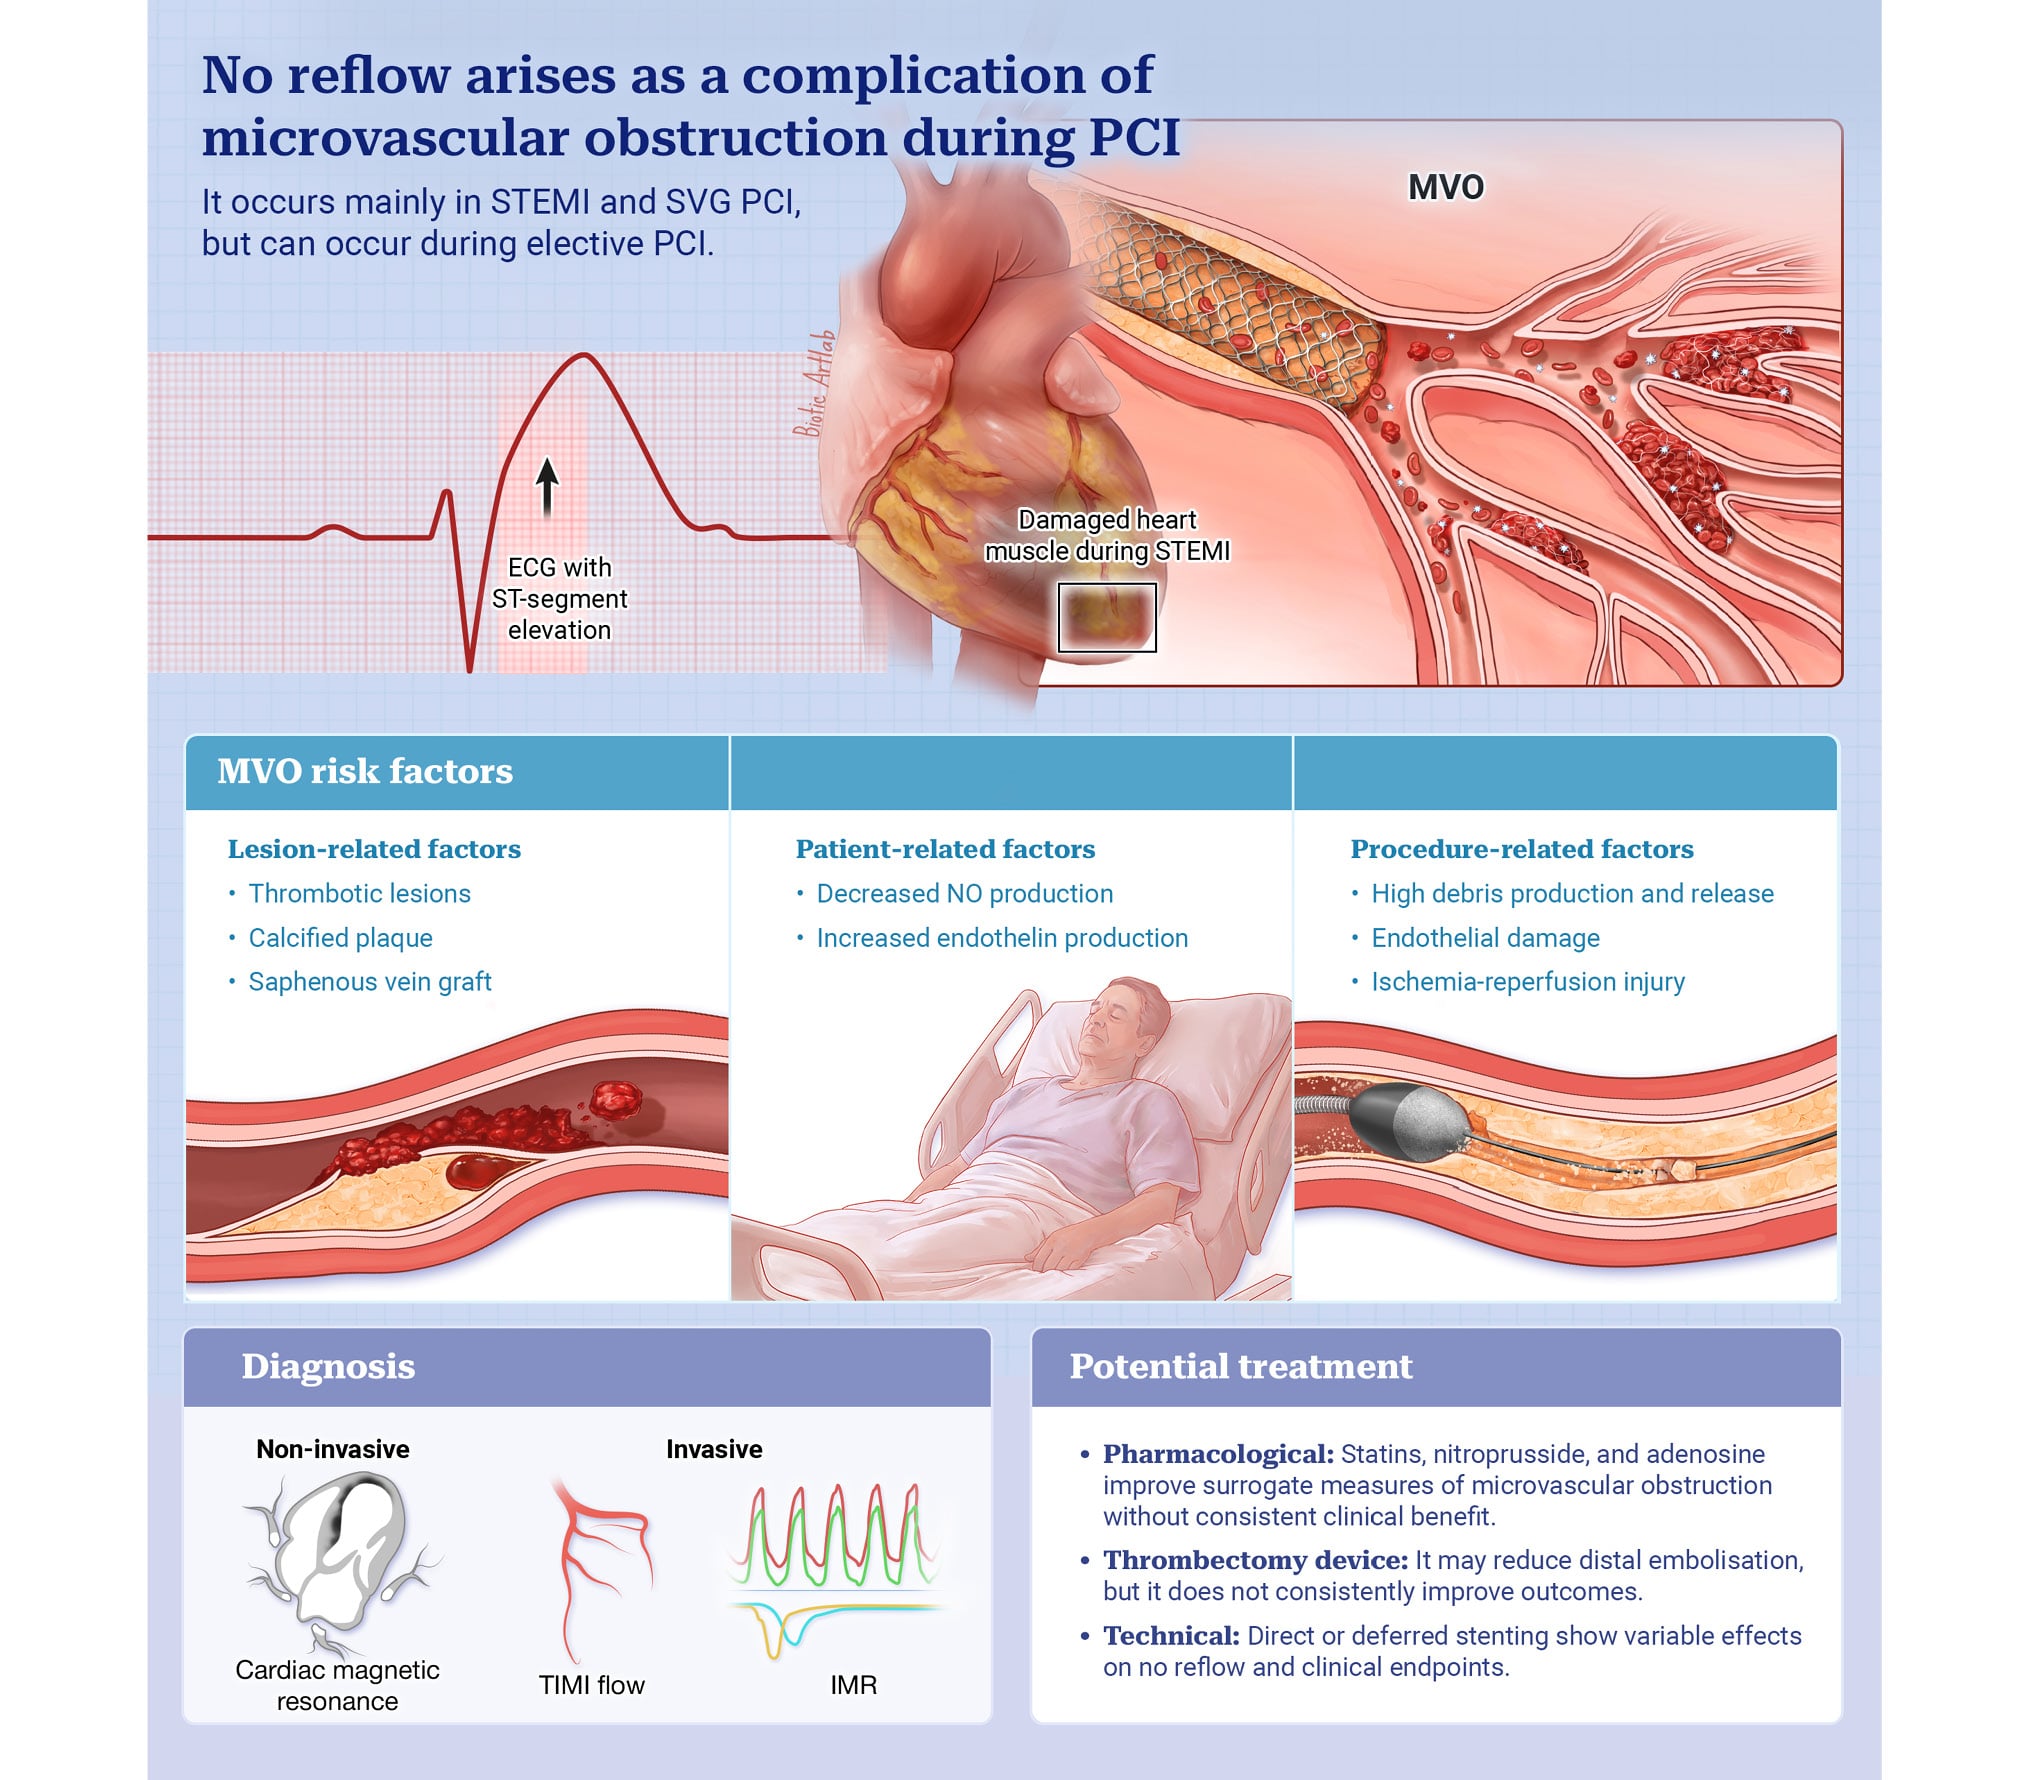
Slow flow and no reflow after percutaneous coronary intervention
eurointervention.pcronline.com
Oct. 28, 2026, 6:42 p.m.
Primary percutaneous coronary intervention is the standard treatment for acute ST-segment elevation myocardial infarction, yet some patients experience the "no-reflow" phenomenon, characterized by inadequate myocardial reperfusion despite successful coronary artery reopening. This condition results from microvascular obstruction caused by multiple factors including myocardial ischemia, distal embolization, and ischemia-reperfusion injury. Occurring in approximately 40-50% of patients undergoing intervention, with higher prevalence in STEMI cases, no-reflow remains a significant clinical challenge. Currently, no consensus exists regarding effective pharmacological or interventional prevention and treatment strategies. This article comprehensively examines the pathophysiology of no-reflow and slow-flow phenomena, exploring established and emerging therapeutic approaches tested in clinical research.
Share on
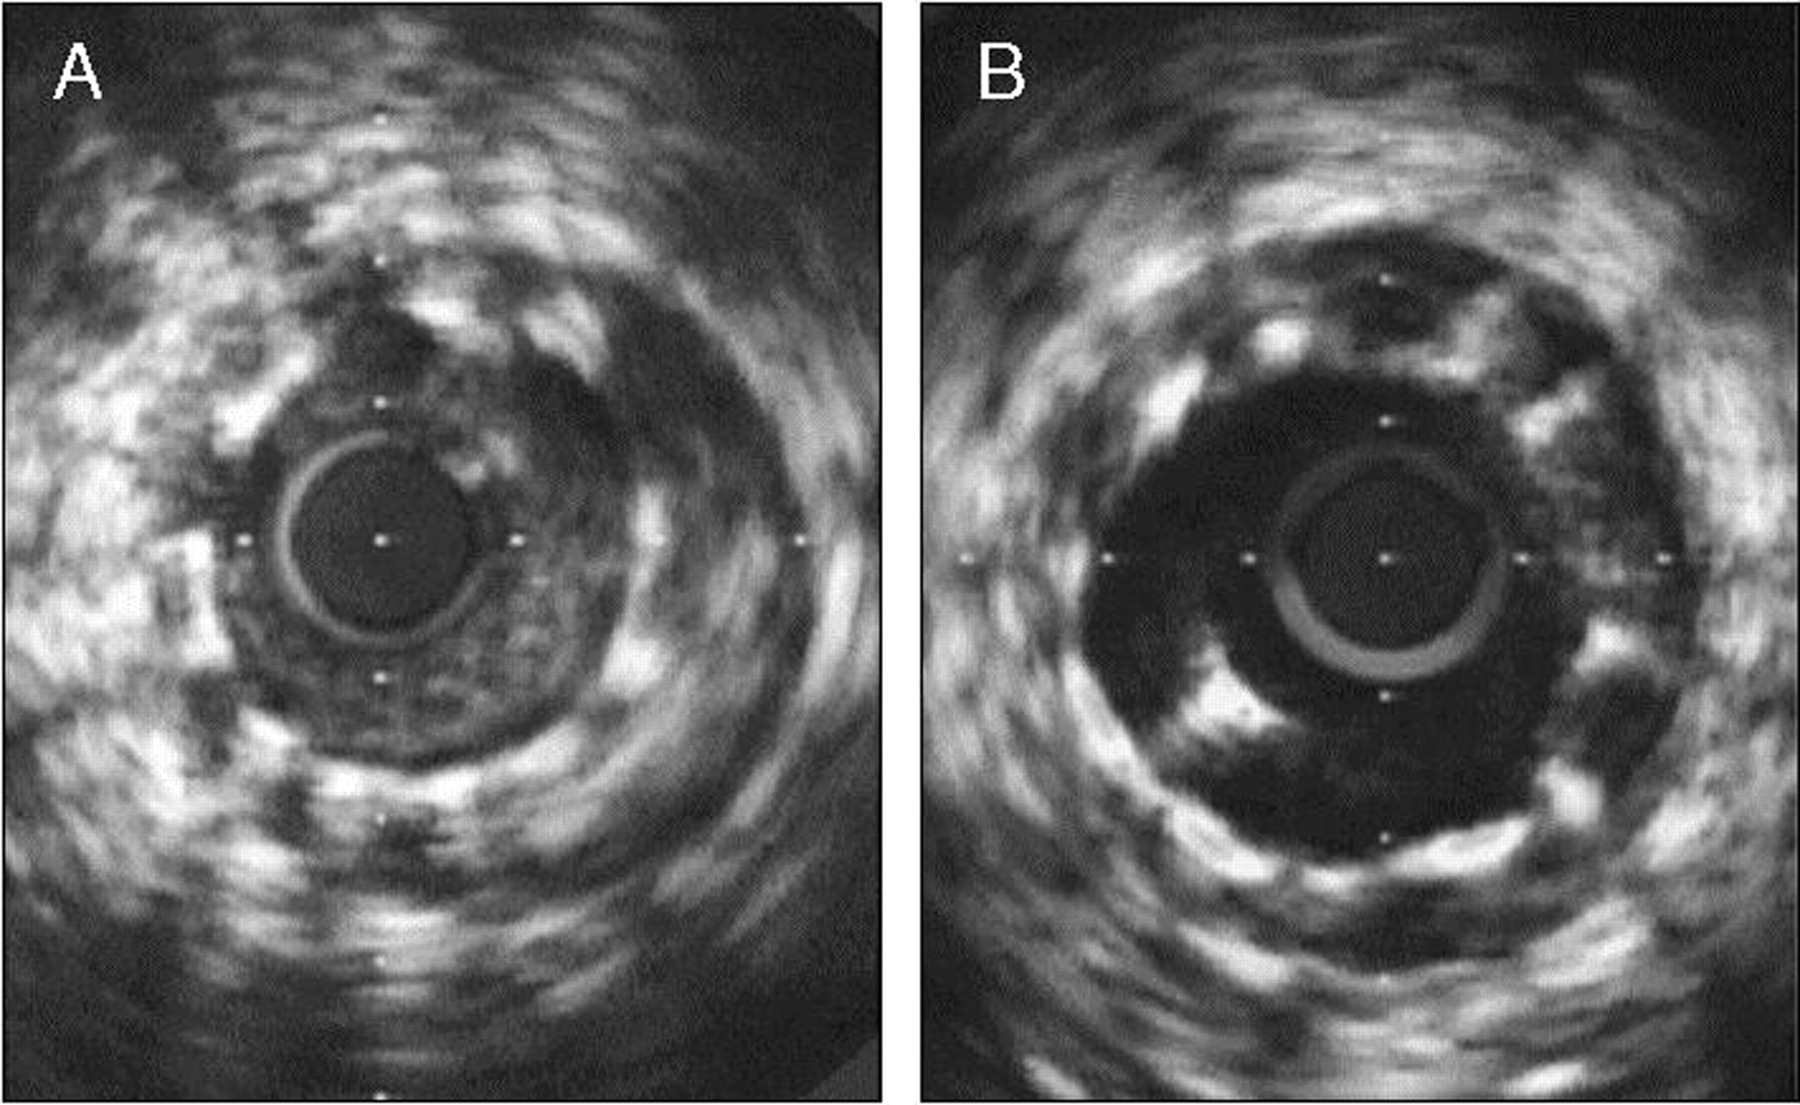
Adoption of intravascular imaging-guided percutaneous coronary intervention in the United States (2012–2022): temporal trends, disparities, and mortality association
www.frontiersin.org
Oct. 28, 2026, 2:07 p.m.
Intravascular imaging (IVI)-guided percutaneous coronary intervention (PCI) using intravascular ultrasound (IVUS) or optical coherence tomography (OCT) has demonstrated improved clinical outcomes, yet US adoption patterns remain understudied. Researchers analyzed 5,220,590 PCI admissions from the National Inpatient Sample between 2012 and 2022 to assess adoption trends, disparities, and clinical outcomes. IVI-guided PCI adoption increased significantly from 7.1% in 2012 to 21.3% in 2022, with minimal demographic disparities but substantial geographic variations—Northeast hospitals led at 27.6% adoption compared to 16.3% in Western facilities. IVI guidance was associated with lower in-hospital mortality (2.32% versus 2.88%) and higher routine discharge rates (84.1% versus 83.7%). After multivariable adjustment and propensity score matching, IVI-guided procedures showed significantly reduced odds of in-hospital mortality (aOR 0.783, 95% CI 0.742–0.827). While IVI adoption continues expanding nationwide, results highlight regional disparities and increased procedural costs alongside improved patient safety outcomes, underscoring the technique's growing clinical importance in contemporary PCI practice.
Angiography-derived versus wire-based fractional flow reserve for guiding coronary revascularization: a meta-analysis of randomized controlled trials
www.frontiersin.org
Oct. 28, 2026, 2:07 p.m.
Researchers conducted a meta-analysis comparing angiography-derived fractional flow reserve (FFR) with traditional wire-based FFR for guiding coronary revascularization decisions. Analyzing four randomized controlled trials encompassing 6,542 patients, the study examined whether angiography-derived FFR—which enables functional coronary assessment from standard angiograms without requiring pressure-wire equipment or adenosine-induced hyperemia—could match wire-based FFR's clinical outcomes. Results revealed no significant differences in major adverse cardiovascular events, all-cause mortality, cardiac mortality, recurrent myocardial infarction, or stent thrombosis between the two approaches. However, angiography-derived FFR was associated with higher percutaneous coronary intervention rates at both patient and lesion levels, plus shorter procedural times. While procedural outcomes were rated as high-certainty evidence, most clinical endpoints achieved only moderate certainty, with trial sequential analysis suggesting insufficient sample sizes for definitive conclusions. The findings suggest angiography-derived FFR provides comparable ischemic outcomes to wire-based FFR while potentially streamlining procedures, though it may increase PCI utilization. Larger, longer-term trials are needed to establish optimal clinical applications and confirm long-term safety profiles.
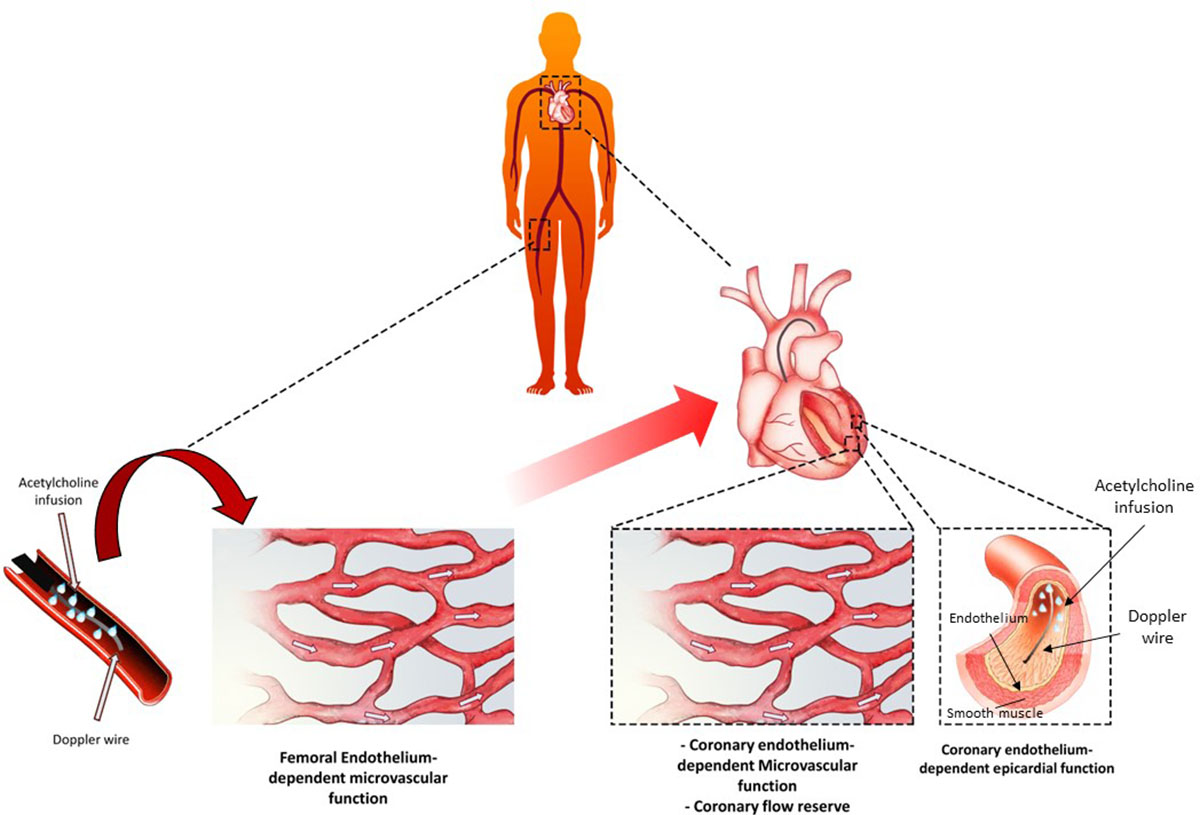
Peripheral microvascular function and in-stent late lumen loss after percutaneous coronary intervention: a retrospective cohort study with an exploratory analysis by implanted stent diameter
www.frontiersin.org
Oct. 28, 2026, 2:07 p.m.
This research article examines the relationship between peripheral microvascular function and in-stent late lumen loss, investigating how small blood vessel health may influence outcomes following coronary stent placement. The study addresses an important clinical question about restenosis—the re-narrowing of stented arteries—which remains a significant complication in interventional cardiology despite advances in stent technology. Researchers evaluated peripheral microvascular dysfunction as a potential predictor of in-stent late lumen loss, analyzing whether systemic vascular changes correlate with localized stent performance. The findings contribute to understanding the pathophysiological mechanisms underlying restenosis and suggest that peripheral microvascular assessment may help identify patients at higher risk for adverse stent outcomes. This work has implications for risk stratification following percutaneous coronary intervention and could inform personalized treatment strategies or enhanced follow-up protocols for vulnerable patient populations.
Quantitative Flow Ratio– vs Angiography-Guided Percutaneous Coronary Intervention: FAVOR III China Three-Year Outcomes
iperfusion.org
Oct. 28, 2026, 2:06 p.m.
Quantitative flow ratio (QFR) is a computational technique that analyzes coronary angiograms to determine whether arterial narrowing functionally limits blood flow, without requiring invasive pressure wires or hyperemic drugs. A prespecified secondary analysis of the FAVOR III China randomized trial, conducted across 26 Chinese centers between December 2018 and January 2020, examined whether QFR-guided percutaneous coronary intervention (PCI) provided benefits for patients with multivessel disease. The study included 3,825 participants with a mean age of 62.7 years, of whom 54% had multivessel disease. Participants were randomized to receive either QFR-guided or standard angiography-guided treatment, with QFR-guided lesions treated when values were 0.80 or below. At three years, QFR-guided PCI demonstrated fewer major adverse cardiac events in multivessel disease patients compared to angiography-guided approaches. However, the treatment effect difference between multivessel and single-vessel disease groups did not reach statistical significance. This analysis contributes to understanding lesion selection for PCI but does not establish QFR equivalence to invasive fractional flow reserve or compare PCI with bypass surgery.
Share on